

Why You May Want to Have a Third Party, and Not Your TPA, “Grade Your Paper”

The Mental Health Parity and Addiction Equity Act (MHPAEA) is a federal law generally requiring plans to have parity in coverage for mental health and substance use disorder treatment (“MH/SUD”) compared to medical and surgical coverage. It was enacted in 2008, amended by the Affordable Care Act (ACA) in 2010, and given “teeth” in the Consolidated Appropriations Act of 2021 (CAA).
The MHPAEA does not require plans to cover MH/SUD benefits, but if they do, MHPAEA likely applies.
A brief overview of “parity.”
As background and very generally, under the MHPAEA, quantitative treatment limitations (QTLs) and non-quantitative treatment limitations (NQTLs) applied to MH/SUD benefits must be comparable in cost, restrictions, and administrative processes to those applied to the medical/surgical benefits.
Quantitative Treatment Limitations and Parity.
QTLs are the financial requirements, such as deductibles, copayments, coinsurance and out-of-pocket limits, and treatment limitations, such as frequency of treatment, number of visits, days of coverage or other similar limits on the scope or duration of coverage. The QTLs applicable to MH/SUD benefits cannot be more restrictive than the predominant requirements or limitations applied to substantially all medical and surgical benefits.
The parity analysis must be applied for each QTL within a coverage tier (e.g., employee, employee plus spouse, etc.) for each of the six classifications of benefits separately. The six classifications of benefits are:
| Inpatient in-network | Outpatient out-of-network |
| Inpatient out-of-network | Emergency care |
| Outpatient in-network | Prescription drugs |
If a type of financial requirement or quantitative treatment limitation applies to substantially all medical / surgical benefits in a classification (e.g., copays apply to substantially all medical and surgical benefits), then it may be permissible for that requirement or limitation (copays) to apply to MH/SUD benefits in the same classification. In some circumstances, plans can subdivide certain classifications to account for multiple network tiers, among other things.
Non-Quantitative Treatment Limitations and Parity.
NQTLs are non-numerical processes, strategies, evidentiary standards, or other criteria that limit the scope or duration of benefits for services provided under the plan. A non-exhaustive list includes: utilization reviews, prior authorizations, step therapies, provider reimbursements, medical management, network tier design, exclusions, and geographical / provider restrictions.
The CAA explicitly requires plans to have a “robust” analysis of NQTL processes, strategies, etc. Essentially, plans must “show their work” giving a robust discussion regarding non-numerical standards and whether the underlying processes, strategies, evidentiary standards, and other factors are comparable and applied no more stringently for MH/SUD benefits than for medical/surgical benefits.
In the 2022 MHPAEA Report to Congress, not a single plan reviewed by the DOL provided sufficient evidence or received a determination of parity.
Employers sponsoring self-insured plans, take note and notice the inherent tension.
Employers sponsoring self-insured plans are responsible, and liable, for MHPAEA compliance. In an effort to assist employers in checking the compliance box, third-party administrators (TPAs) either proactively or upon request are giving employers their plan’s analysis. Interestingly, every analysis from a TPA to an employer has concluded that the employer’s plan passes NQTL analysis. Contrastingly, every analysis reported by the agencies in the 2022 report to Congress said that insufficient support and documentation was given to the agencies to make a determination, and, moreover, corrective actions were sought in many plans that were reviewed.
What does this mean? Well, it’s reasonable to conclude that an unbiased third party might serve as an appropriate arbiter for compliance. True, the cost for such analysis will be more than “free.” However, the results could add value to the plan and those participating in it while simultaneously mitigating the risk of exposure to litigation, agency involvement, or bad press.
Common areas of noncompliance requiring corrective action.
The current areas of agency focus seem to be restrictions or disparities in autism and ABA therapies, provider reimbursements, nutritional counseling, and residential treatment centers.
In April, the DOL released a blog highlighting its findings and what it’s accomplished in the area of Autism:
- EBSA’s Los Angeles Regional Office investigated a large service provider that excluded coverage for ABA therapy in hundreds of self-insured plans. EBSA’s investigation resulted in 3 plans removing exclusion for ABA therapy and offering coverage for that benefit moving forward, affecting more than 18,000 participants and their beneficiaries.
- An investigation by EBSA’s Chicago and Dallas Regional Offices into an ABA therapy exclusion resulted in a large claims administrator adding ABA therapy as a default coverage option for all of its self-insured plans. This correction resulted in the elimination of the exclusion for ABA therapy for autism for nearly one million participants.
- After a Seattle family encountered difficulty communicating with their health plan regarding claims for their child, an EBSA Benefits Advisor stepped in to assist. The plan reprocessed the claims, resulting in an additional $20,000 of coverage.
- Another parent contacted an EBSA Benefits Advisor in the Dallas Regional Office for assistance with claims that had not been paid. After the Advisor contacted the plan to resolve the issue, this family received approximately $24,000 they were owed.
If you are interested in learning more about MHPAEA analysis, reach out to me here.
If you sponsored a self-insured or level-funded plan, including an HRA, with a plan year beginning on or after February 1, 2021, keep reading!

What is the PCORI fee?
The Patient-Centered Outcomes Research Institute (PCORI) fee is a fee that plans are required to pay to fund research on the comparative effectiveness of medical treatments. Essentially, every covered life on a medical plan has a value earmarked for such research funding every year.
Are any plans exempted from paying the PCORI fee?
Yes, but the general rule is if you are sponsoring a major medical plan that covers individuals living in the United States, you are subject to the PCORI fee. This includes tax-exempt and ERISA-exempt plans. These are the limited exceptions:
- Plans that are designed to cover employees who are working and residing outside the United States
- Dental and vision plans, known as excepted benefits
- Employee assistance programs (EAPs)
- Wellness and disease management programs
Who Pays the PCORI Fee?
- For fully insured plans, the fee is paid by the carriers.
- For employers sponsoring self-insured or level-funded plans, the Employer / Plan Sponsor pays the fee.
- For employers sponsoring a Health Reimbursement Account (HRA) integrated with a fully insured plan, the Employer / Plan Sponsor pays the fee for the HRA (self-funded plan) and the carrier pays the fee on the major medical plan.
The Employer / Plan Sponsor is responsible for reporting the PCORI fee on the self-insured plan. This is not something that can be delegated to another entity.
When is the PCORI Fee due?
The PCORI fee is due no later than July 31 of the year following the year in which the plan ends. This is why employers sponsoring non-calendar year self-insured plans renewing in 2021 have a reporting obligation July 31, 2023. It’s easy to forget! Here’s a non-calendar year and calendar year example:
| Plan Year: | February 1, 2021 to January 31, 2022. |
| PCORI Due: | July 31, 2023 – the year following the year the plan ends. |
Calendar-year plans (1.1 – 12.31) that renewed January 1, 2022 report their fee no later than July 31, 2023.
| Plan Year: | January 1, 2022 to December 31, 2022 |
| PCORI Due: | July 31, 2023 – the year following the year the plan ends. |
What is the policy year / plan year?
Generally, the policy / plan year is the 12-month period of medical coverage. There are nuances, so feel free to reach out to me with questions.
Why is the Plan Year relevant?
It matters because the PCORI fee is an indexed amount that is determined by the last day of your plan / policy year.
What if we had a short plan year in 2021 or 2022?
The PCORI fee applies to a short plan year, and the employer is responsible for paying the PCORI fee on the short plan year if the plan was self-insured. Here’s an example:
- Employer sponsored self-insured medical plan that ran on a non-calendar year basis, July 1 to June 30.
- In 2022, Employer moved the plan to a calendar year to line up with its Cafeteria Plan year. The plan had a short plan year of July 1, 2022 to December 31, 2022.
- For this PCORI reporting cycle, Employer has two plan years for which to account:
- July 1, 2021 to June 30, 2022
- July 1, 2022 to December 31, 2022
How much is the PCORI Fee?
Generally, the PCORI fee is calculated by multiplying the average number of covered lives (“belly buttons”) on the self-insured medical plan by $2.00 indexed. The indexed amounts for this reporting period are:
- $2.79 for plans that ended on or after October 1, 2021, and before October 1, 2022
- $3.00 for plans that ended on or after October 1, 2022 through December 31, 2022
Using our example above:
- Original Plan Year Fee: July 1, 2021 to June 30, 2022 → $2.79 per covered life
- Short Plan Year Fee: July 1, 2022 to December 31, 2022 → $3.00 per covered life
What if we sponsor a self-insured medical plan, prescription plan, and an HRA?
If the employer sponsors multiple self-insured plans (i.e., medical, prescription drugs, an HRA), this can be treated as one plan for purposes of calculating the PCORI fee.
What if we sponsor a fully insured medical plan with an integrated HRA?
There is a special rule for HRAs that are paired with a fully insured medical plan. Remember, the carrier is paying the PCORI fee on the fully insured plan. You have
How do we determine the average number of “covered lives”?
There are three methods available to determine the number of covered lives, which is reported on the Form 720. They are:
- Actual Count: Add the total number of lives covered for each day of the first nine months of the plan year and divide that total by the number of days in the first nine months.
- Snapshot Count: Add the total number of lives covered on any date during the same corresponding month in each of the first three quarters of the plan year, and divide that total by the number of dates on which a count was made.
- Form 5500 Method: Add the number of participants on the first day of the plan year and the last day of the plan year as reported on Form 5500 and divide by 2. This method can only be used if you file a Form 5500 that covers the applicable reporting period and if that Form 5500 was filed timely.
The goal is to use the calculation method that results in the smallest number thereby reducing the PCORI fee.
Are COBRA Qualified Beneficiaries included in the covered lives calculation?
How is the PCORI fee reported?
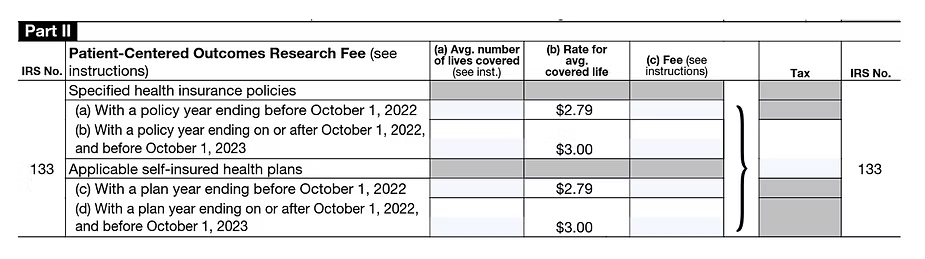
The PCORI fee is reported in Part II, line 133, of Form 720, found here. The updated Form 720 (rev. June 2023) contains the applicable indexed fee amounts of $2.79 for plans that ended on or after October 1, 2021, and before October 1, 2022, and $3.00 for plans that ended on or after October 1, 2022 through December 31, 2022. Yes, it goes to October 1, 2023, but plans ending in 2023 aren’t yet reporting or paying the PCORI fee.
How is the PCORI Fee paid?
Deposits aren’t required for this fee, so employers aren’t required to pay the fee using EFTPS. However, if the fee is paid using EFTPS, the payment should be applied to the second quarter.
Is the PCORI Fee deductible?
Yes. The PCORI fee is deductible under the Internal Revenue Code section 162.
What kind of documentation should an Employer keep?
The IRS may request records substantiating the PCORI fee going back four years from the date of the last payment. Another agency involved in PCORI, the U.S. Department of Health and Human Services (HHS), can go back 10 years for records pertaining to employee counts and fees.
What happens if a payment was missed?
Employers responsible for fee payments are subject to the PCORI fee plus an excise tax ranging from 5% of the PCORI fee up to 25% of the fee.
What if we still have questions?
I am happy to address any questions you may have. Please reach out via the contact form.

Direct primary care models (DPC) and high deductible health plans (HDHPs) offer, among other things, cost-savings to employers and their participants. And, while pairing the two could be a dynamic duo, adding an HSA component is generally not a good idea.
Unless structured where participants pay fair market value for non-preventive care services (as defined by the IRS) prior to satisfying the statutory minimum deductible, the HDHP is not HSA-compatible.
And, let’s face it…why fret on designing a plan that is theoretically HSA-compatible if the employer isn’t contributing to the HSA in a meaningful way, the employees don’t understand the long-term potential of the HSA, and – perhaps most importantly – the participants sacrifice their health in the short-term because they can’t afford the FMV / “self-pay” costs of getting care.
Sure, the Affordable Care Act (ACA) is over 10 years old, and, for the most part, the Employer Mandate (also known as Pay or Play or the Employer Shared Responsibility) is old news. However, there is a big change that may cause some growing pains for employers of all sizes, particularly those who offered a self-insured medical plan during 2023.
When we say “self-insured,” this includes employers sponsoring level-funded health plans, self-funded, partially self-funded, or ICHRAs (Individual Coverage HRAs) at any time during the prior year (2023).
Here, we will give you the long and short of what you need to know to have a successful 2024 ACA’s Employer Mandate filing season

Laying the Foundation: Two Potential Penalties for Employers with a Filing Obligation.
There are two potential ways to trigger a penalty under the Internal Revenue Code (Code) each filing season. (There are two other penalties for Applicable Large Employers – ALEs – under Code 4980H, but that’s for a later discussion.)
- Failure to File
Employers sponsoring a self-insured group health plan at any time during the prior calendar year have a filing obligation the following year – regardless of size!
Employers sponsoring a self-insured group health plan at any time during the prior calendar year have a filing obligation the following year – regardless of size!
The ACA added Code Section 6055, which requires every provider of minimum essential coverage to report information of covered individuals by filing information returns (Form 1095) with the IRS. Plan sponsors of self-insured plans are “providers of coverage.” While this has always been the case, we fear many non-ALE (under 50) employers sponsoring level-funded plans may find this to be new news to them.
Section 6056 requires ALEs file a more detailed Form 1095 (1095-C) specifying information about their offers of coverage to full-time employees and their dependents and the adequacy (affordable and/or minimum value) of that coverage.
The deadline to file is April 1, 2024. - Failure to Furnish
Code Section 6055 requires every provider of coverage to furnish individual statements. Keep reading for some practical ways to satisfy this requirement.
The deadline to furnish is March 1, 2024.
BIG Change! Mandatory E-Filing for (almost) All Employers Offering Self-Insured Plans.- Old 250-Return Threshold: Prior to this 2024 reporting season, employers could use paper filing with the IRS for up to 249 forms of a single type. Once there were 250 forms of the same type, the employer had to file electronically for that form type.
- New 10-Return Threshold: Beginning this year, mandatory electronic filing (e-filing) is required for ten (10) or more returns of different types. The aggregate rule includes Forms W-2, 1099, 1094-B, 1094-C, 1095-B, and 1095-C as part of the 10-return threshold.
This is a major ACA compliance change especially for non-ALEs (those employers who had less than 50 full-time equivalent employees) who sponsor self-insured plans. With the popularity of level-funded plans in the small group market, many employers (and brokers) will be in shock to learn that they are (and have been) required to file Forms 1094-B and 1095-B (“B Forms”) with the IRS and must now do so electronically. Employers should check with their Third Party Vendor or TPA to see if they will be the reporting entity.
Failure to follow these electronic filing requirements comes with a hefty price tag! Generally, employers are subject to a penalty amount of $310 per Form unless reasonable cause can be established. The first 10 ACA forms filed by paper do not incur the penalty.
The deadline to electronically file with the IRS is April 1, 2024.
Filing electronically with the IRS is a process that takes time, a transmitter control code (TCC), and testing. We won’t bore you with the technicalities, but we do offer a solution.

Reminder: Automatic Extension to Furnish Forms.
In years prior to 2023, January 31 was the deadline to furnish Forms 1095 to individuals with the opportunity to file a request for a 30-day extension. Beginning with 2023, an automatic 30-day extension is granted for furnishing. With 2024 being a leap year, the deadline to furnish Forms 1095s to individuals is March 1, 2024.
Different Ways to Fulfill the Furnish Requirement.
- Non-ALEs. With the individual mandate being $0, the IRS allows non-ALE employers to furnish Forms 1095-B by posting a clear and conspicuous Notice on its Home Page stating, “Tax Information” which links to a page that includes a statement in all caps, “IMPORTANT HEALTH COVERAGE TAX DOCUMENTS”, as an example. The Notice should state that individuals may receive a copy of their 1095 upon request and include the email address, the physical address, and phone number to the contact to whom the request must be made. The Notice must be posted by March 1, 2024, and must retain the website through October 15, 2024.
- ALEs. Employers furnishing forms 1095-C to individuals must secure an affirmative consent to distribute in an electronic manner – either by website, portal, or email attachment. Importantly, this opt-in consent must be separate from the consent to receive plan information under ERISA. Also, the safe harbor for electronic distribution does not apply, as this is a tax document and not a health plan notice.
StanleyKup offers a sample affirmative consent for employers to tailor to meet their electronic distribution requirements for Form 1095-C.
Updates on ACA Penalties for Applicable Large Employers
The IRS recently released revised penalty amounts for the Affordable Care Act’s Employer Shared Responsibility provisions for 2025. Commonly known as ACA Pay or Play Penalties, the IRS unveiled the adjusted amounts on February 12th 2024.
Employers with over 50 full-time equivalent employees (Applicable Large Employers (ALEs)) face potential penalties if they fail to offer adequate coverage. The adjusted penalties for 2025 have decreased slightly from the previous year.
- Under section Section 4980H (a) the penalty is now $2900 compared to 2024’s $2970. This penalty is levied when an employer fails to provide group health coverage to a minimum of 95% of its full-time employees.
- Under Section 4980H (b) the penalty will be $4350, compared to 2024’s $4460. This one is applied when an employer offers coverage that is either unaffordable or does not meet minimum value standards.
Employers must remain vigilant about ACA reporting requirements for the 2023 tax year, and it’s crucial for them to carefully assess their group health plan offerings for 2024 to avoid the penalties mentioned here.
The Remote Workforce: States with an Individual Mandate.
While the federal Individual Mandate is $0, several states continue to impose an Individual Mandate on their citizens. Employers with employee(s) who worked or resided in California, Rhode Island, New Jersey, Massachusetts, Vermont, or the District of Columbia at any time in 2023 may have a state filing and furnishing requirement. Most states use the same Form 1095 and require a filing with a state department, but Massachusetts uses its own Form 1099-HC. Filing deadlines vary by state.
StanleyKup Compliance has a Solution for ACA Reporting!
StanleyKup Compliance offers ACA and State Individual Mandate solutions! We work with employers of any size to ensure timely submissions and compliance with the new regulations.
For assistance reporting, filing, and distributing your Forms, simply visit https://www.stanleykup.com/aca-reporting
As individuals confront the complex world of healthcare, many find themselves playing financial hopscotch over deductibles and navigating the tightrope of out-of-pocket limits, not to mention the costs of essential health care services.
But what if there was a way to incentivize cost-saving behavior while simultaneously enhancing healthcare affordability and accessibility? Enter Texas H.B. 2002, passed unanimously during a public hearing in 2023.
The Dawn of a New Era: H.B. 2002 Unveiled
Amending current law, Texas H.B. 2002, introduced a groundbreaking provision that allows individuals to credit out-of-pocket cash payments for out-of-network medically necessary services and supplies towards their deductible and maximum out-of-pocket expenses. This revolutionary measure introduced by the House Health Care Reform Select Committee, extends a lifeline to consumers, empowering them to make informed decisions regarding their medical care while alleviating the burden of exorbitant out-of-pocket costs.

Getting Even Further into the Specifics
Beginning with fully insured policies effective on or after January 1, 2024, H.B. 2002 mandates insurers to credit any out-of-pocket payments made directly to a physician or healthcare provider for covered medical or health services towards an insured’s deductible and annual maximum out-of-pocket expenses covered by a PPO health plan.
In addition, this legislative session tasked insurers with establishing a streamlined procedure for individuals to claim these credits in line with the Texas Department of Insurance’s rules. Insurers are also required to make sure that all necessary documentation to support such claims is readily accessible to policyholders on their respective online platforms. Consumers should check carrier websites to see about carrier forms. (We don’t think they are inclined to send out a Public Service Announcement on this!! Shocking.)
Side Bar: What does this mean for Texans?
Start with the Texas Two Step:
- You have to find out if your plan is fully insured or self-insured/level-funded. Eligibility of a person is ONLY based on having a fully insured plan.
- You have to be covered under a PPO plan, not an HMO plan.
Then, do your homework and use the tools available to you.
- Make sure the service(s) you seek are covered by your health benefit plans. If it’s not covered in-network, it won’t be covered out-of-network.
- Use the price shopping tools provided by your insurance. You can even call your insurance and see what it would cost to go in-network for your upcoming service. When talking or searching, try to get CPT and/or diagnostic insurance codes! This is what your insurance will use to see if it’s covered and, if it is, the “average discounted rate” they would have paid for an in-network service.
Next, call your provider and negotiate a cash price up-front. Try something like this:
- “Hi, Dr. I really want to continue seeing you but you’re out of my plan’s network. I saw that my insurance would cover a routine visit (CPT 99211) as an established patient for $325 if you were in my network. Since you’re not, can I offer you $320 cash?
Practical Tip: The provision applies when your bill is not sent to the insurance company, and the amount you paid to the doctor or healthcare provider is lower than what your insurance company usually pays to their preferred providers for the same service or item. That is a big deal! Now, you are able to navigate the landscape with greater ease and financial prudence.

Embracing the Future: The Impact of H.B. 2022
The implications of this legislation go beyond mere text, serving as a catalyst for enhancing healthcare affordability and accessibility. By incentivizing individuals to seek out cost-effective alternatives and facilitating greater transparency in healthcare pricing, the bill encourages informed decision-making and financial prudence among healthcare consumers. This in turn fosters a healthcare ecosystem characterized by improved patient satisfaction, bolstered consumer choice, and enhanced well-being.
Looking Ahead: Implementation and Beyond
On January 1st 2024, H.B 2002 came into effect. The collaboration and active engagement of insurers, healthcare providers and, most importantly, individuals is paramount to harness the full potential of this transformative legislation. With ever-increasing healthcare costs, especially felt by our small and mid-size fully insured employer-sponsored health insurance, H.B 2002 has been applauded as a beacon of opportunity for other states to consider ways to affirmatively assist consumers at the point of sale.